Came across this study and would love to know others' thoughts. I have been following the progress of the ketogenic (almost no carbohydrate) diet for some time and its potential value in glioblastoma and epilepsy. This study seems to show that some of the purported benefits could be achieved through a ketone ester supplement, which serves to provide the brain with its alternative non-glucose fuel source (Ketone bodies)
direct link to abstract: https://academic.oup.com/neuro-oncology/article-abstract/20/suppl_6/vi36/5154383?redirectedFrom=fulltext )
Any thoughts on this, and how it might be translated to human use?
Thanks!
Wednesday, 24 July 2019

Alternative to Bosellia Wokvel?
I've seen previous posts explaining the rationale behind the recommendation of Boswellia (WokVel) preparation. However, this formulation is currently out of stock from all suppliers in my area (UK). I note from Ben Williams' book that the dose of boswellia used in the cited German trial (showing reduced oedema) was 4200 mg/day, which is much higher than the 999mg suggested on this site. What's the best alternative to WokVel, given that I am unable to source it? I assume that taking it alongside Celecoxib is tried-and-tested?
Monday, 22 July 2019
Do statins, ACE inhibitors or sartans improve outcome in primary glioblastoma?
Hello all,
I spotted this paper and thought it was best to share: “Do statins, ACE inhibitors or sartans improve outcome in primary glioblastoma?” Although I’ve not read the full paper, it’s worth noting that they concluded:
I spotted this paper and thought it was best to share: “Do statins, ACE inhibitors or sartans improve outcome in primary glioblastoma?” Although I’ve not read the full paper, it’s worth noting that they concluded:
This secondary analysis of two large glioblastoma trials thus was unable to detect evidence for an association of the use of statins, ACEI or sartans with outcome in patients with newly diagnosed glioblastomaShould we abandon ACE inhibitors, etc?
Seeing feedback on proposed treatment plan and drug/ supplement cocktail
Hi Stephen,
I finally have medical data back for my dad and we had our first meeting with his oncology teams yesterday. I have summarized his medical data as well as our treatment plan below.
A couple of notes and questions upfront:
-
I didn't see anything on my dad's medical records about MGMT
-
Would greatly appreciate your feedback on the proposed drug cocktail and supplements
-
Are we missing anything?/ Dosages?
-
I would like to supplement COC protocol with some additional re-purposed drugs (particularly the first 4 in the table below. Do you have any information on dosage and how others go about getting prescriptions for these?
-
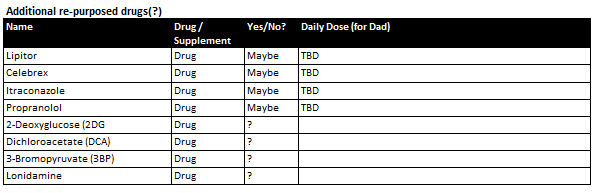
Many thanks again for your continued help.
Silvia
MEDICAL DATA:
-
Clinical synopsis
-
64M p/w expressive dyphasia and headache with likely malignant transformation of L) temporal LGG
-
2018 June generalised seizure diagnosed with left temporal mass likely LGG
-
Monitored as outpatient
-
Started on keppra and phenytoin for seizure control (self ceased keppra in
 January due to rash)
-
Last seizure in April
-
July 2019 clinical synopsis
-
Presented with headaches and expressive dyphasia
-
Treatment
-
Stereotactic left temporal craniotomy and debulking of glioma (3 July)
-
Good postoperative course
-
Discharged 11 July
-
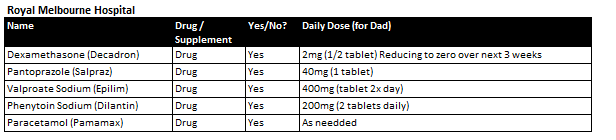
Medications
-
Histopathology results
-
Final Diagnosis: Left insula lesion: Glioblastoma. Features in keeping with IDH wild type (WHO grade IV)
-
GFAP positive
-
IDH-1 R132H negative (not mutated)
-
ATRX positive (not mutated)
-
P53 positive
-
P16 CDKN2A negative
-
Topoisomerase - approximately 20%
-
Post operative MRI
-
Small focus of residual enhancing tumour at the posterosuperior resection margin. Extensive oedema with midline shift measuring 9mm to the right and left uncal herniation has slightly improved
-
Recommending SOC treatment
-
Radiation / chemo to begin in ~3 weeks (~12 August)
-
Combined radiation & TMZ
-
Confirming targeted cavity and margin, not whole brain
-
Starting with 3 week course as patient is over 60
-
If patient is fit will recommend more aggressive 6 week treatment (TBD)
-
Followed by TMZ maintenance schedule
OUR CURRENT PLAN
-
Commence SOC protocol as prescribed by medical team in ~3 weeks
-
Complement with
-
(1) Ketogenic Diet
-
Strict 4:1 ratio, targeting Glucose / Ketone Index of 1:2 or lower (ideally 1:1 at 3mmol/ L each)
-
Calorie restricted ~900kcal/ day
-
Intermittent fasting (work towards target 2 - 8pm eating window)
-
Supplemented with Exogenous ketones (Caprilic acid and BHB salts during fasting window and can also be consumed during eating window)
-
(2) Repurposed drugs cocktail per Care Oncology Clinic (submitted info, waiting for treatment plan)
-

-
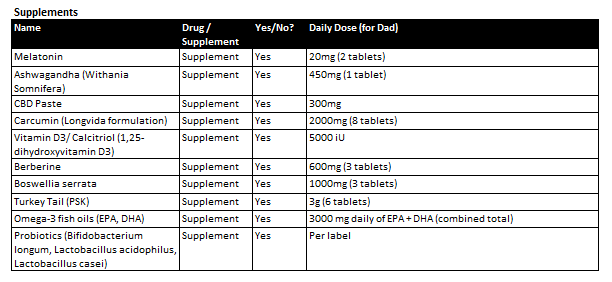
(3) Supplements
-
I didn't see anything on my dad's medical records about MGMT
Would greatly appreciate your feedback on the proposed drug cocktail and supplements
- Are we missing anything?/ Dosages?
- I would like to supplement COC protocol with some additional re-purposed drugs (particularly the first 4 in the table below. Do you have any information on dosage and how others go about getting prescriptions for these?
Clinical synopsis
- 64M p/w expressive dyphasia and headache with likely malignant transformation of L) temporal LGG
- 2018 June generalised seizure diagnosed with left temporal mass likely LGG
- Monitored as outpatient
- Started on keppra and phenytoin for seizure control (self ceased keppra in
- Last seizure in April
- July 2019 clinical synopsis
- Presented with headaches and expressive dyphasia
- Treatment
- Stereotactic left temporal craniotomy and debulking of glioma (3 July)
- Good postoperative course
- Discharged 11 July
- Medications
Histopathology results
- Final Diagnosis: Left insula lesion: Glioblastoma. Features in keeping with IDH wild type (WHO grade IV)
- GFAP positive
- IDH-1 R132H negative (not mutated)
- ATRX positive (not mutated)
- P53 positive
- P16 CDKN2A negative
- Topoisomerase - approximately 20%
Post operative MRI
- Small focus of residual enhancing tumour at the posterosuperior resection margin. Extensive oedema with midline shift measuring 9mm to the right and left uncal herniation has slightly improved
Recommending SOC treatment
- Radiation / chemo to begin in ~3 weeks (~12 August)
- Combined radiation & TMZ
- Confirming targeted cavity and margin, not whole brain
- Starting with 3 week course as patient is over 60
- If patient is fit will recommend more aggressive 6 week treatment (TBD)
- Followed by TMZ maintenance schedule
Commence SOC protocol as prescribed by medical team in ~3 weeks
Complement with
- (1) Ketogenic Diet
- Strict 4:1 ratio, targeting Glucose / Ketone Index of 1:2 or lower (ideally 1:1 at 3mmol/ L each)
- Calorie restricted ~900kcal/ day
- Intermittent fasting (work towards target 2 - 8pm eating window)
- Supplemented with Exogenous ketones (Caprilic acid and BHB salts during fasting window and can also be consumed during eating window)
- (2) Repurposed drugs cocktail per Care Oncology Clinic (submitted info, waiting for treatment plan)
- (3) Supplements
Sunday, 21 July 2019
Curcumin preparation type?
Apologies if this is going over some issues previously discussed: There are lots of different curcumin pills and potions around, and 1000-2000 mg+ (Longvida) has been recommended elsewhere on this site. There seems to be a world of difference in how much curcumin gets into the brain depending on in what form it is taken.
I wondered on what basis is Longvida's product recommended? I noticed this 2015 conference presentation: "Intratumoral bioavailability and changes in Phosphoethanolamin-MRI of the solubilised natural compound curcumin in glioblastoma patients", which demonstrated how curcumin accumulated in glioblastoma tumours when it was given orally as "solubilisated curcumin". With a bit of internet searching using the terms in this study description, it seems to be that they used NovaSOL curcumin, or something very similar ("Micelle solubilized curcuma extract") I'm not sure how the doses used in the study (apparently a total of 3g of solubilized curcumin per day, which sounds like a heck of a lot!) equates to the NovaSOL capsules that can be bought (each of which contains just '30mg Curcuminoids and 5.4μg Vitamin D' ). Less certain again is how this might equate to an actual clinical effect on the tumour when combined with chemotherapy, although the likes of review articles such as 'Curcumin for the Treatment of Glioblastoma' would say that it is definitely worthwhile adding to the mix.
All input greatly received from cocktail-makers!
Thanks,
Stu
Stu
Saturday, 20 July 2019
Nicotine and brain tumour growth
Has the topic of nicotine (and other stimulants) been considered by the collective community?
My grade 2 astrocytoma was recently found to have advanced to grade 3(after 11years). Now IDH mutant, 1p / 19q not-codeleted, MGMT methylated. Both nicotine (via lozenges) and coffee are helpful in fighting fatigue and helping concentration.
Any thoughts? I am naturally concerned about taking anything that may hinder radiotherapy and chemotherapy (due to start at the beginning of August).
Thanks!
Stu
My grade 2 astrocytoma was recently found to have advanced to grade 3(after 11years). Now IDH mutant, 1p / 19q not-codeleted, MGMT methylated. Both nicotine (via lozenges) and coffee are helpful in fighting fatigue and helping concentration.
Any thoughts? I am naturally concerned about taking anything that may hinder radiotherapy and chemotherapy (due to start at the beginning of August).
Thanks!
Stu
Monday, 15 July 2019
IDH1+ GBM recurrence--any help appreciated!
Hi, I have found Stephen and many of you to be great sources of information over the years and would really appreciate any help. (Unfortunately, I can post but not comment thru some weird glitch.) I have given my son's background before, but briefly he is a 26 y/o with secondary GBM (IDH1+) which was found to have recurred on a scan today. He was diagnosed with AO2 (or perhaps AA3) in 2011 and had not quite total resection, "left-over" resected in 2012 and then had proton therapy as part of a clinical trial. He did well for over 5 years--graduated from college and started med school. He had a very small recurrence found 1/18 that had mutated to GBM (hypomutated with no actionable mutations other than IDH1 per Foundation One) with a very total resection. He had never had any chemo and we opted to use a PARP inhibitor (BGB-290) with temozolamide--started 4/18. He returned to medical school on chemo--tolerated both pretty well. Today found out that 3 mm area of "uncertain significance" found 7 weeks ago is now 2.6x2x2.7 cm and near a ventricle (though some of size likely incorporates scar). So, trying to figure out the next step.
He was offered TMZ and radiation as options. He wants to have the tumor "debulked", which seems supported in the medical literature. (His tumor is left frontal lobe.)
Options we have considered: TOCA (thru IST program maybe?) with proton
LITT with pembro
AZD-1390 trial --since ATM/ATR inhibitors useful if IDH1?
Duke Poliovirus--only works 21% and no better if mutant
(Of course, I don't know if he will qualify for any of these.)
Would very much appreciate any suggestions! Marcia
He was offered TMZ and radiation as options. He wants to have the tumor "debulked", which seems supported in the medical literature. (His tumor is left frontal lobe.)
Options we have considered: TOCA (thru IST program maybe?) with proton
LITT with pembro
AZD-1390 trial --since ATM/ATR inhibitors useful if IDH1?
Duke Poliovirus--only works 21% and no better if mutant
(Of course, I don't know if he will qualify for any of these.)
Would very much appreciate any suggestions! Marcia
Newly Diagnosed GBM
Hi all,
My name is Silvia, I am new to this community and a week ago knew nothing about GBM. I'm incredibly grateful for the wealth of information here and would like to thank everyone in advance for your support.
My 64 father was diagnosed with glioblastoma last week. He had a subtotal resection on July 3rd which was successful in removing ~95% of the solid part of his tumor. He is recovering well and was discharged from hospital on July 11th.
My 64 father was diagnosed with glioblastoma last week. He had a subtotal resection on July 3rd which was successful in removing ~95% of the solid part of his tumor. He is recovering well and was discharged from hospital on July 11th.
He is based in
Melbourne Australia and is being treated by the team at Royal Melbourne
Hospital, who are recommending the radiation/TMZ protocol. I am still
waiting for them to send me his medical data but our current plan is the
following
- Press-Pulse
protocol as a
neoadjuvant treatment while he is recovering from surgery with the hope
that if there is improvement in his MRI we can delay chemo/radiation
- Details of the protocol:
- Based off the metabolic
theory of cancer
- Press (ongoing):
- Ketogenic Diet with
intermittent fasting supplemented with exogenous ketones
- Low dose metformin
- Pulse:
- Hyperbaric Oxygen
therapy
- High dose IV vitamin C
- Cancer
specific glycolytic inhibitors: (e.g. 2-Deoxyglucose (2DG),
Dichloroacetate (DCA), 3-Bromopyruvate (3BP); Lonidamine)
- insulin
potentiation
- https://nutritionandmetabolism.biomedcentral.com/articles/10.1186/s12986-017-0178-2
- https://peterattiamd.com/domdagostino/ [Dom
describes the protocol for GBM at 1:59:45]
- https://www.frontiersin.org/articles/10.3389/fnut.2018.00020/full
- Repurposed Drug/ Supplement
cocktail
- Will post details of this to
get feedback once I have his detailed diagnosis and a consultation with
the Care Oncology Clinic
- Proceed with radiation/ chemo
if no improvement in MRI prior to planned start date
I have a few questions
for now:
- Has anyone in this community tried the press-pulse protocol and if so how (what parts, neoadjuvant/ concurrent/ adjuvant with SOC etc.?) and with what result? Does anyone know of any practitioners located in Australia that might be able to help in implementing the protocol?
- Has anyone had any experience
with the Burzynski clinic / Antineoplastons? (https://www.burzynskiclinic.com/)
·
For context: My mum
and dad are very against radiation and chemo, and unfortunately subscribe to
big pharma conspiracy theories. They are searching for information on youtube
which means that on top of the research I am doing myself, I must also spend a
lot of time researching and more often than not debunking the “cures” they come
across
·
The quick research
I've done on this seems to suggest it's controversial and unproven
- Does anyone know if there is any harm with Laetrile (Vitamin B17 /Amygdalin)? I know there is no evidence to support its efficacy but my mum is convinced it will help and I wonder if its worth fighting her on it if it doesn't do any harm (she's currently giving him apricot kernels ~ 40-50 / day)
- Similarly with Phour Salts?
Thank you all in advance for any information you might be able to share!
Silvia
Saturday, 13 July 2019
Question About D-Dimer Blood Test
Hello All,
Does anyone have good knowledge on D-Dimer and its importance? I understand that there can sometimes be false positives on results, but if a D-Dimer reading came back super high should the patient go in for a scan right away for clots? The range is .20-.45, my Uncle's just came back at 2.25. Any advice appreciated.
Thank You ~
Does anyone have good knowledge on D-Dimer and its importance? I understand that there can sometimes be false positives on results, but if a D-Dimer reading came back super high should the patient go in for a scan right away for clots? The range is .20-.45, my Uncle's just came back at 2.25. Any advice appreciated.
Thank You ~
Tuesday, 9 July 2019
Antioxidant use in IDH1 mutant tumors
I'd like to open a topic up for debate here regarding antioxidant use in IDH1 mutant tumors. My understanding is that IDH1 mutant tumors are characterized by generally low Glutathione (antioxidant) levels, significantly sensitizing them to ROS generation. Some researchers speculate that this is the primary reason for superior OS stats for IDH1 mutant tumors, e.g.:
Given this particular dynamic, should I conclude that use of antioxidants which stimulate Glutathione (e.g. Alpha Lipoic Acid, Green tea, Cinnamon,...) should better be avoided in the case of IDH1 mutant tumors?
I am particularly interested in this question as my tumor is IDH1 mutated, and I recently started taking the Metabloc protocol (Alpha Lipoic Acid + Hydroxycitrate), since it seems to deliver very promising synergy with Metformin use. After investigating a bit, I am contemplating skipping the Alpha Lipoic Acid, however.
Any thoughts on this topic? Thanks!
John
Wednesday, 19 June 2019
Boswellia during radiation
Hi Stephen/others,
Do you think it is a bad idea to use Boswellia during radiation? - A week ago I started Boswellia Serrata Extract (Wokvel) 333mg three times a day after having a seizure on radiation day #11 out of 30 sessions. There is the thought that the radiation and Temodar 180mg daily are causing some edema. I have started taking keppra 500mg in AM and 750mg in PM. I am not on any steroids(dexamethasone). I have been told that research has shown signs of Boswellia having pretty strong antioxidant properties- but I do not have the source(s) for that thought. So now I am concerned that Boswellia may not be great to take right now if it could interfere with the radiation treatments?
Also, I don’t know if I should actively pursue changing to Valproic Acid to capture any potential benefits it could have as a radio-sensitizer? Any opinion?
Thanks,
Mike
Tuesday, 11 June 2019
Saturday, 8 June 2019
New cocktail - feedback much appreciated
Hello everyone. This website is amazing and I wish I had found it sooner. My brother who is 46 has GBM, grade IV, IDH-1 wild type, MGMT unmethylated. No other genetic data currently. He has finished his first six weeks of radiotherapy and TMZ and is now in a 4 week break until starting monthly TMZ again. We are in the UK and he is on the current ipilimumab clinical trial that is running.
We have put together the cocktail listed below from information we have read. I would be really grateful for any feedback anyone has on this. In particular, is there anything missing and do the doses sound high enough - I am wondering if the curcumin should be higher for example. Also, we have not included Boswellia currently - is Boswellia something that should be included irrespective of steroid use?
The below list is all non-prescription. Being in the UK, it seems to be difficult to get off label stuff prescribed. It would be great to hear from anyone who has managed this in the UK. I would be interested to hear from anyone that has been able to get e.g. Tamoxifen or Antabuse prescribed.
Cocktail
The items marked with * are things have been suggested to us for generally boosting the immune system, the others are specific to GBM.
| Item | Dosage per day |
| Berberine | 1500mg - 500mg 3 times a day half an hour before meals |
| Bio- Curcumin BCM 95 (meant to deliver 7x more bio-active curcumin) | 1200mg –
400mg 3 times a day with meals |
| Bio-Quinone Active Q10 (ubiquinone (coenzyme Q10)* | 400mg – 100mg
4 times a day with food |
| Bio-SelenoPrecise (selenium) | 200ug – 1 capsule
a day. |
| Enzymatic Therapy Cell Forte with IP-6 and Inositol* | 4 capsules a
day which contain in total: Calcium 260mg Phosporus 380mg Magnesium 80mg IP-6 1600mg Inositol 440mg |
| Fish oil (source of omega 3 fatty acids) – EPA and DHA | 2000mg Fish
Oil per serving (2 capsules) 660mg EPA and 440mg DHA. |
| Genistein- Isoflavone derived from soy products | 1 capsule
per day: Novasoy® Soy isoflavone concentrate (Non-GMO) 135 mg Standardized to 40% isoflavones 54 mg Soynatto® Fermented Soyfood (organic, Non-GMO) 435 mg |
| Green tea extract | 1 capsule
per day: Green tea decaffeinated extract (leaf) [std. to 98% polyphenols by UV (710.5 mg), 45% EGCG by HPLC (326.25 mg)] 725 mg |
| Immutone (shark liver oil)* | 1000mg a day |
| Maitake D fraction extract | 60 drops –
20 drops 3 times a day between meals |
| Melatonin | 20mg at
night |
| Moducare (pro Vitamin D5, plant sterols and sterolins) * | 3 capsules a
day on empty stomach |
| Quercetin | 500mg per
day. 1 capsule in morning |
| Resveratrol | 1000mg –
500mg 2 times a day |
| Salvestrol Platinum * | 900mg – 450mg
2 times a day with food |
| Silibinin (ingredient of milk thistle) | 2 capsules in
morning which contain (in total) 316mg of silymarins (silibinin). |
| Syno-Vital
(Oral Hyaluronic Acid plus vitamin C) * |
1 sachet a day |
| Vitamin D3 | 1 capsule a
day - 5,000IU |
Many thanks in advance.
Wednesday, 29 May 2019
Avastin + (Temodal or CCNU)?
Dear all
I’ve finally receive the test report for my father, however
I am not sure to what extent are these results reliable, and what is the best
way to go from now on based on this report. I highly appreciate your advice. We
just started the Avestin (10 mg/kg) while being in our second cycle of Temodal
due to hug oedema (left temporal, biopsy-only, facing left eye ptosis few days
after the first cycle of Temodal)
Reports in the nutshell: MGMT methylated (36%), EGFR amplified,
IDH wildtype, Tert (Mutant for C250T, wildtype for C228T), 1P/19q (does not carry deletion of the genetic region 1p/19q), CMV negative (FFTP
tissue block)
1) How to decide when to stop Avastin, if ever?
2) Shall we reduce the Avastin dosage if we are going to stop
it after a short period?
3) Whether after stopping it, the temodal+ccnu can be still a
good option for us?
4) Shall we change temodal to CCNU now that we are facing
decline in his situation? Or is it better to wait until the end of 3rd
cycle, do the MRS and then decide?
5) Any cocktail
advice while we are starting Avestin? Maybe captopril and chloroquine (sadly, I just know about
EGFR and not the EGFRviii)
(his current Neutrophil
is 6600 and Platelets 89000, sleeping most of the time in the last 12 days, 20 minutes’
walk everyday)
Semi-Cocktail: metformin 500 (just to hopefully
prevent diabetes on dexa), CurcuMIND 2, Boswellia wokvel 3, acetazolamide 500, Keppra
750, valproate 500, Ranitidin 3, sulforaphane 1, Marrow plus (soon would be added
3), folic acid 1.
Report (the reason for quoting these in length is
mostly because I feel it could be helpful for other ppl in my situation to know
to what extant these tests are similar to what is done in other countries and maybe
it can help them saving more time and money. Sorry for the length, we can
delete it if it is inappropriate)
FFPT tissue block:
Positive for MGMT methylation (36.25% of methylation for
all 4 CpG sites):
Genomic DNA was obtained from tissue using the Qiagen kit. The
quality/quantity of the DNA was estimated in a Nanodrop spectrophotometer.
The MGMT methylation status was measured by Pyrosequencing
technology for 4 CpG islands within the methylated promoter region of the MGMT
encoding sequence.
Positive for EGFR amplification (approximately 11-fold
larger)
DNA was extracted using the QIAamp FFPE DNA kit. EGFR gene
amplification was analyzed by real-time PCR standard primers and probe using
Lightcycler 480 II instrument.
Comparing to the normal copy number of control gene, EGFR
gene was amplified in this sample.
Tert (Mutant for C250T, wildtype for C228T)
(QIAamp® DNA FFPE DNA Kit)
Allele Specific PCR was performed for amplification of TERT promoter mutations
(C228T, C250 T) by ABI Veriti instrument. Sequencing of PCR product were
performed via Pyromark Q96 instrument and analyzed to detect Polymorphism.
Wildtype for IDH1
(c.394-396 [R132H and variants])/ Wildtype for IDH2 (c.514-516 [R172K
and R140Q and variants])
DNA extracted by FFPE QIAGEN kit and a segment of DNA containing
IDH1 exon 2 and IDH2 exon 4 is amplified using ellele specific PCR primers and
Pyrosequencing data at codons 132, 140 and 172 respectively, is interpreted by
a pathologist.
CMV negative (FFTP tissue block)
DNA was extracted using the Qiagen DNA micro kit and
qualitative Real time PCR has been done using Taq-Man Probe assay to detect of
viral nucleic acid.
1P/19q (the assayed sample does not carry deletion of the
genetic region 1p/19q)
FISH analysis was performed on a section from a paraffin
embedded tissue block using differentially labeled fluorescent probes targeting
1p36/1q25 and 19p13/19q13.
The fluorescence in situ hybridization on the paraffin
tissue was positive for a co-deletion of 1p/19q. (???)FISh was performed
using probes for the target at 1p36 and 19q13 and control probes at 1q25 and
19p13.
Monday, 27 May 2019
Anaplastic Astrocytoma Grade 3
Hi Everyone,
My husband is considering starting Radiation/Chemotherapy combination to treat the Anaplastic Astrocytoma Grade 3 (located in right hemisphere) and I would like some feedback on your experience and suggestions for additional cocktails.
Here is a timeline and the current diagnosis:
My husband is considering starting Radiation/Chemotherapy combination to treat the Anaplastic Astrocytoma Grade 3 (located in right hemisphere) and I would like some feedback on your experience and suggestions for additional cocktails.
Here is a timeline and the current diagnosis:
- May 2001 - First craniotomy and at that time it was diagnosed as Astrocytoma Grade 2
- September 2013 - Second craniotomy and diagnosis as Anaplastic Oligoastrocytoma Grade 3
- August 2018 - Third craniotomy and diagnosis Anaplastic Astrocytoma Grade 3, IDH1 mutated, ATRX mutated, MGMT methylated, 1 P19Q no LOH detectable, proliferation index mib-1 to 10%
He never wanted to do Radiation/Chemo due to concerns of long term effects, so after the second surgery, he had declined further treatment. During this time he did not take any constant supplements but did do Ketogenic diet for about 2 years. The concern was always not to have some side effects.
He recently had another MRI check and it shows a further progression of the remaining tumor. The biggest part of the tumor is located in an area where they cannot operate without causing handicap. His left arm is already damaged and is showing signs of difficulty with walking (left leg) as the tumor is pressing on those fibers.
With all of your experience, I would like your feedback on where should we start. I am reading other posts to come up with a list of possible supplements.
He is almost 40 and we live in Switzerland.
Thank you for your feedback.
N
Sunday, 26 May 2019
Gamma Tile Radiation
Stephen, has Gamma Tiles been discussed on site here for recurrent GBM? This is an awesome, very informative video. What are your thoughts?
Thanks,
Candy
https://www.facebook.com/Braintumor/videos/10157370996799485/UzpfSTY4MTUxNTYxMTpWSzo5MzgwNTg0Mzk4NjcwOTU/
https://www.cancer.umn.edu/node/17171
Thanks,
Candy
https://www.facebook.com/Braintumor/videos/10157370996799485/UzpfSTY4MTUxNTYxMTpWSzo5MzgwNTg0Mzk4NjcwOTU/
https://www.cancer.umn.edu/node/17171
Saturday, 25 May 2019
Meds during radiation + daily TMZ
In the library, the “A” list shows these meds may be beneficial during radiation:
Chloroquine,CBD/THC,Celebrex,Boswellia, DCA, Disulfiram, and Pterostilbene. Doer this mean that the other “A” list meds should be avoided during a combined treatment of radiation/TMZ?
Thanks,
Mike B
Friday, 24 May 2019
Vladimir’s
healing cocktail
Hello to everyone!
I’ve just learnt about this great blog and would like
to get some useful information and advice about my father-in-law’s treatment.
Vladimir M., 71 years.
He was diagnosed with glioblastoma (Grade IV), frontal
area, size 52 mm*39 mm *23mm, operated on 21/05/19. After the resection, he was
O’K. I mean he could speak, walk, he remembered everything. At the moment he is
receiving dexamethasone injections (4 mg./3 times a day).
Histology results:
- glioblastoma;
- positive reaction to GFAP;
- Ki-67 index - 25%;
- negative to SYN, IDH, ki-67 10-12%
- negative to SYN, IDH, ki-67 10-12%
Now we are waiting for radiation and TMZ (probably
started in 2 weeks).
I’m a little bit frustrated at the moment about what medicine to start
with to make the treatment most effective. Stephen’s list contains such a lot
of drugs that I cannot decide which of them should be included in our drug
cocktail.
What do you think about this cocktail?
Drug
|
Dosage
|
For how long time should
the patient take these drugs?
|
Keppra
|
1000 mg.
|
|
hydroxychloroquine
|
400mg daily
|
|
Metformin
|
500mg
|
|
Celebrex
|
200-400mg daily
|
|
Mebendezole
100 mg for 3 months + Doxycycline 100 mg for 1 month
|
Do we actually need it or
it’s excessive?
|
Supplements
|
Dosage
|
|
Boswellia
(Wokvel Brand)
|
500-1000mg
|
|
Green
Tea or Extract
|
700 mg 40% EGCG
|
|
Molybdenum
Glycenate
|
1g
|
|
Berberine
|
500-100mg daily
(divided doses)
|
|
Melatonin
|
10-20 mg.
|
|
Omega
3 Fish Oil
|
tbd
|
|
Probiotic
|
tbd
|
|
Quercetin
|
865
mg
|
|
Bromelain
|
500
mg
|
|
Marrow
Plus
|
tbd
|
|
Milk
thistle
|
1000-2000mg
|
1) Is there anything you
would suggest I add or remove?
2) When do we have to
start taking these drugs? Right now or during radiation?
3) Is it OK if we start
taking supplements a week later after the drugs (I need some time to get them
from USA to Russia)?
Thanks to everyone for your help
Subscribe to:
Posts (Atom)